Measuring Brain Health, and Where a Blood Draw Fits

Measuring brain health comes down to three kinds of evidence: a person's own report, a score on structured tasks, and a laboratory reading from a biological sample. On October 7, Ian H. Robertson of the Center for BrainHealth at the University of Texas at Dallas published a piece in Psychology Today arguing that brain health can follow the path cardiovascular health has taken since 1950. The argument is a good one, and it is more demanding than it first sounds. Cardiovascular medicine earned its standing in a specific order, and that order ends with a laboratory test and a controlled trial.
So the analogy is worth taking seriously by anyone selling a brain health program, including us.
The demands of the heart analogy
Robertson's case rests on the Center for BrainHealth's own three-year study, "Measuring and increasing the brain health span across adulthood: a public health imperative." Lori G. Cook, Jeffrey S. Spence, Sandra Bond Chapman and colleagues published it in Scientific Reports on May 2, 2026, and it is registered at ClinicalTrials.gov as NCT04869111. It followed 3,966 adults aged 19 to 94, assessed every six months over three years, using a composite called the BrainHealth Index with three factors: Clarity, Connectedness, and Emotional Balance. The authors report that the overall index and all three factors rose over the three years, with higher engagement in the program associated with larger change.
The most useful sentence in that paper describes the purpose of the index. The authors write that it "functions as a personalized benchmark against which to measure improvement or loss rather than as a diagnostic classifier," and they compare it to a functional fitness battery, interpreted against a person's own baseline. That is a careful description and it is the correct one. The Psychology Today piece puts the same idea in plainer language, describing the index as a metric similar to a VO2 max measure of fitness.
Hold that beside the tools cardiovascular medicine has. A VO2 max test is a performance measure, and cardiology did not get where it is on performance measures alone.
Cardiovascular medicine built it in a specific order
Three steps, and the sequence is the argument.
First came long-running population studies that watched large groups of people for decades and named the conditions that traveled with disease. The Framingham Heart Study, begun in 1948 with 5,209 residents of one Massachusetts town, is the one that identified high blood pressure and high blood cholesterol as major risk factors for cardiovascular disease.
Second came a cheap laboratory measurement of those factors, repeatable on an ordinary morning, reported by an accredited laboratory, and comparable between one person and another. A lipid panel takes one draw and produces numbers a clinician reads the same way in any city.
Third came randomized controlled trials asking the question the first two steps cannot answer: the effect on people when the measurement is changed on purpose. Those trials turned a lipid panel into a number that changes a patient's decisions.
Brain health has a good start on step one. The Scientific Reports study is three years long and nearly four thousand people deep, and work of that size has been rare in this category. Step two is thin. Step three, for structured brain health programs, is mostly unfinished, ours included.
Measuring brain health: the three answers a program can give
A program can offer three kinds of evidence that something changed, and it helps to know which one you are being handed.
The first is self-report, where a person answers questions about their own thinking, mood, sleep, or daily function. It is cheap, it scales, and it captures something real that no instrument sees. It also moves when a person believes they are being helped, which is a known property of joining any program.
The second is a performance battery, where a person does structured tasks and is scored. This is the kind of measure a VO2 max comparison points at, and it is a genuine step up from asking. Its limit is the far-transfer question, which is the oldest argument in this field.
The clearest illustration of that limit comes from the largest randomized trial in cognitive training. ACTIVE, Advanced Cognitive Training for Independent and Vital Elderly, enrolled 2,832 older adults and assigned them to memory, reasoning, or speed-of-processing training, or to a control group. Its ten-year follow-up was published in the Journal of the American Geriatrics Society in January 2014. At ten years, participants in all three training groups reported less difficulty with everyday tasks than controls. When the researchers measured everyday functioning with performance-based tests instead of asking about it, the paper reports weak to absent effects. Two measures of the same thing, in the same trial, pointing different ways.
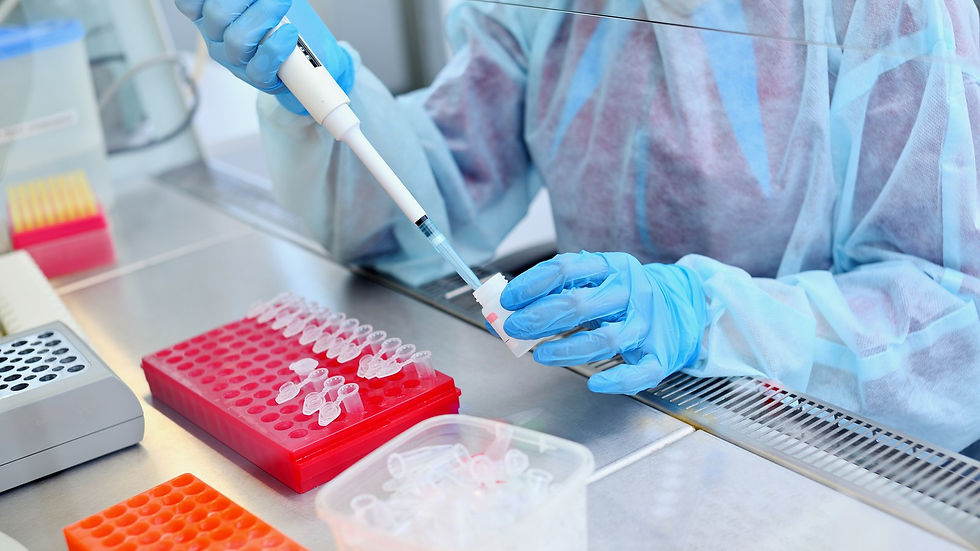
The third is laboratory measurement, where something in a biological sample is quantified by a laboratory operating under its own quality system. It answers a narrower question than the other two, and it answers it without asking the participant anything.
Observes | Cannot establish | Reported by | Repeat frequency | |
Self-report | A person's own account of thinking, mood, and daily function | That measured performance changed; it moves with expectation | The person, scored by the program | As often as asked, with expectation effects building |
Performance battery | A person's score on structured tasks at a set time | That a score gain follows the person into a shift, a classroom, or a kitchen | The program, against its own norms | Limited by practice effects on the tasks |
Laboratory measurement | A quantity in a biological sample | The cause of any change, and anything about the brain directly | An accredited laboratory under its quality system | As often as a draw is acceptable, limited by cost |
Every row loses something. A program that shows you one row and calls it measurement is showing you a third of the picture.
The four questions blood leaves open
The gap ACTIVE found between people's reports and their test results is the reason Neurova Labs added a laboratory measure. The iXpressGenes CoreSignals Panel reads 22 markers of RNA gene expression from whole blood, and it is designed to track inflammatory and immune signals associated with stress and recovery. It is not used to diagnose any condition. The laboratory is CLIA-certified and CAP-accredited, which means a third party with no interest in our results runs the assay and stands behind the numbers.
That is worth something, and four limits sit on it, all four stated on our measurement page.
It does not measure the brain. The panel reads signals in whole blood, and blood is not brain tissue. Anyone who tells you a blood test reads a brain is overselling a real measurement.
It cannot be attributed to one cause. The same inflammatory and immune signals move with sleep, exertion, illness, and stress. A reading is a reading, and naming its cause is a separate claim that needs evidence of its own.
It records that a value moved. Explaining the movement takes more, and a single-arm design cannot separate a program from everything else happening in a person's life between one draw and the next.
It carries no finding from any regulator. Neurova Academy is a general wellness and cognitive training program. It is not a medical device, it is not FDA approved or cleared, and the panel is not a diagnostic test.
Neurova Labs, and the work ahead
Our own figures come from observational pilot cohorts, and every one we publish carries its participant count and its study design in the same sentence. A controlled validation study is underway here. Until it reports, we hold step one and a piece of step two, and we are missing step three.
It is worth describing the top of that ladder, so the rungs below it are legible. The 2026 Nobel Prize in Physiology or Medicine, announced on October 5, went to Karl Deisseroth of Stanford, Peter Hegemann of Humboldt University of Berlin, and Georg Nagel of the University of Würzburg. The prize recognized optogenetics, a method that switches a defined population of neurons on and off with light and observes the behavior that follows. That design supports causal conclusions no observational study can reach. Randomized controlled trials in people sit below it. Single-arm studies sit below those.
Neurova Labs makes no causal or mechanistic claim, and nothing above belongs to us. We report our measurements, name the design behind them, and say which questions a controlled study would settle. The four things we will not claim are set out on our claims page.
Five questions for any program about its evidence
These work on any vendor in this category, including us.
Which of the three kinds of measurement produced this number, and did a participant supply it?
Was there a control group, and were people assigned to it at random?
Was the thing measured the ability that was trained, or something the training was supposed to carry into daily life?
If a laboratory value is quoted, which laboratory ran it, which body accredits it, and which other factors move that value?
Which result would count as evidence that your program did not work?
The last one is the most useful question in the list. A program that cannot answer it has not designed a test it could fail.
If you find anything on our site that contradicts this page, write to info@neurovalabs.com and we will fix the other one.
Neurova Academy is a general wellness and cognitive training program. It is not a medical device and is not offered to diagnose, treat, cure, or mitigate any disease or condition, including concussion, traumatic brain injury, or CTE. Outcomes described reflect observational pilot findings and individual experience, and are not a prediction of results for anyone else. Individual results vary. Laboratory testing provided by iXpressGenes, a CLIA-certified, CAP-accredited laboratory. References to published research, prizes, and government publications are for commentary only and do not imply endorsement of Neurova Labs by any federal entity, research institution, or awarding body.
Media contact: info@neurovalabs.com


Comments